

Why the old fixes keep tripping us up
I remember a night in Elmhurst, Queens—lights flickering, nurses juggling IV stands—when three out of sixty infusion pumps hiccuped mid-shift; that surge (5% failure) cost three hours of bedside improvisation, a real wake-up call—what do you do when the gear bends but the patient can’t? medical equipment manufacturing companie was on my mind that night. As a medical equipment manufacturer with over 15 years in the B2B supply chain, I’ve seen the same band-aid moves: bolt-on QA checks, last-minute CNC machining runs, and rushed sterilization cycles that barely meet ISO 13485 paperwork. I’ll be blunt—those fixes feel janky, no cap. They patch the symptom, not the supply-chain bleed.

What exactly failed on the floor?
I dig into specifics because I don’t do fluff: the pumps were an infusion pump model X-200, shipped in February, and returned for rework by March 2023 after intermittent valve faults. I know the metrics—QA/QC logs showed a 2–3% drift in torque specs, PCB assembly tolerances off by 0.1 mm—and that cascaded into downtime and urgent recalls. I’ve run audits with OEMs in Brooklyn and Staten Island; I’ve watched CE marking paperwork sit while engineers scramble to fix firmware bugs. The hidden pain? Operators get blamed; procurement gets handcuffed; patients wait. (That’s the ugly middle.)
Building for tomorrow: a lean, technical roadmap
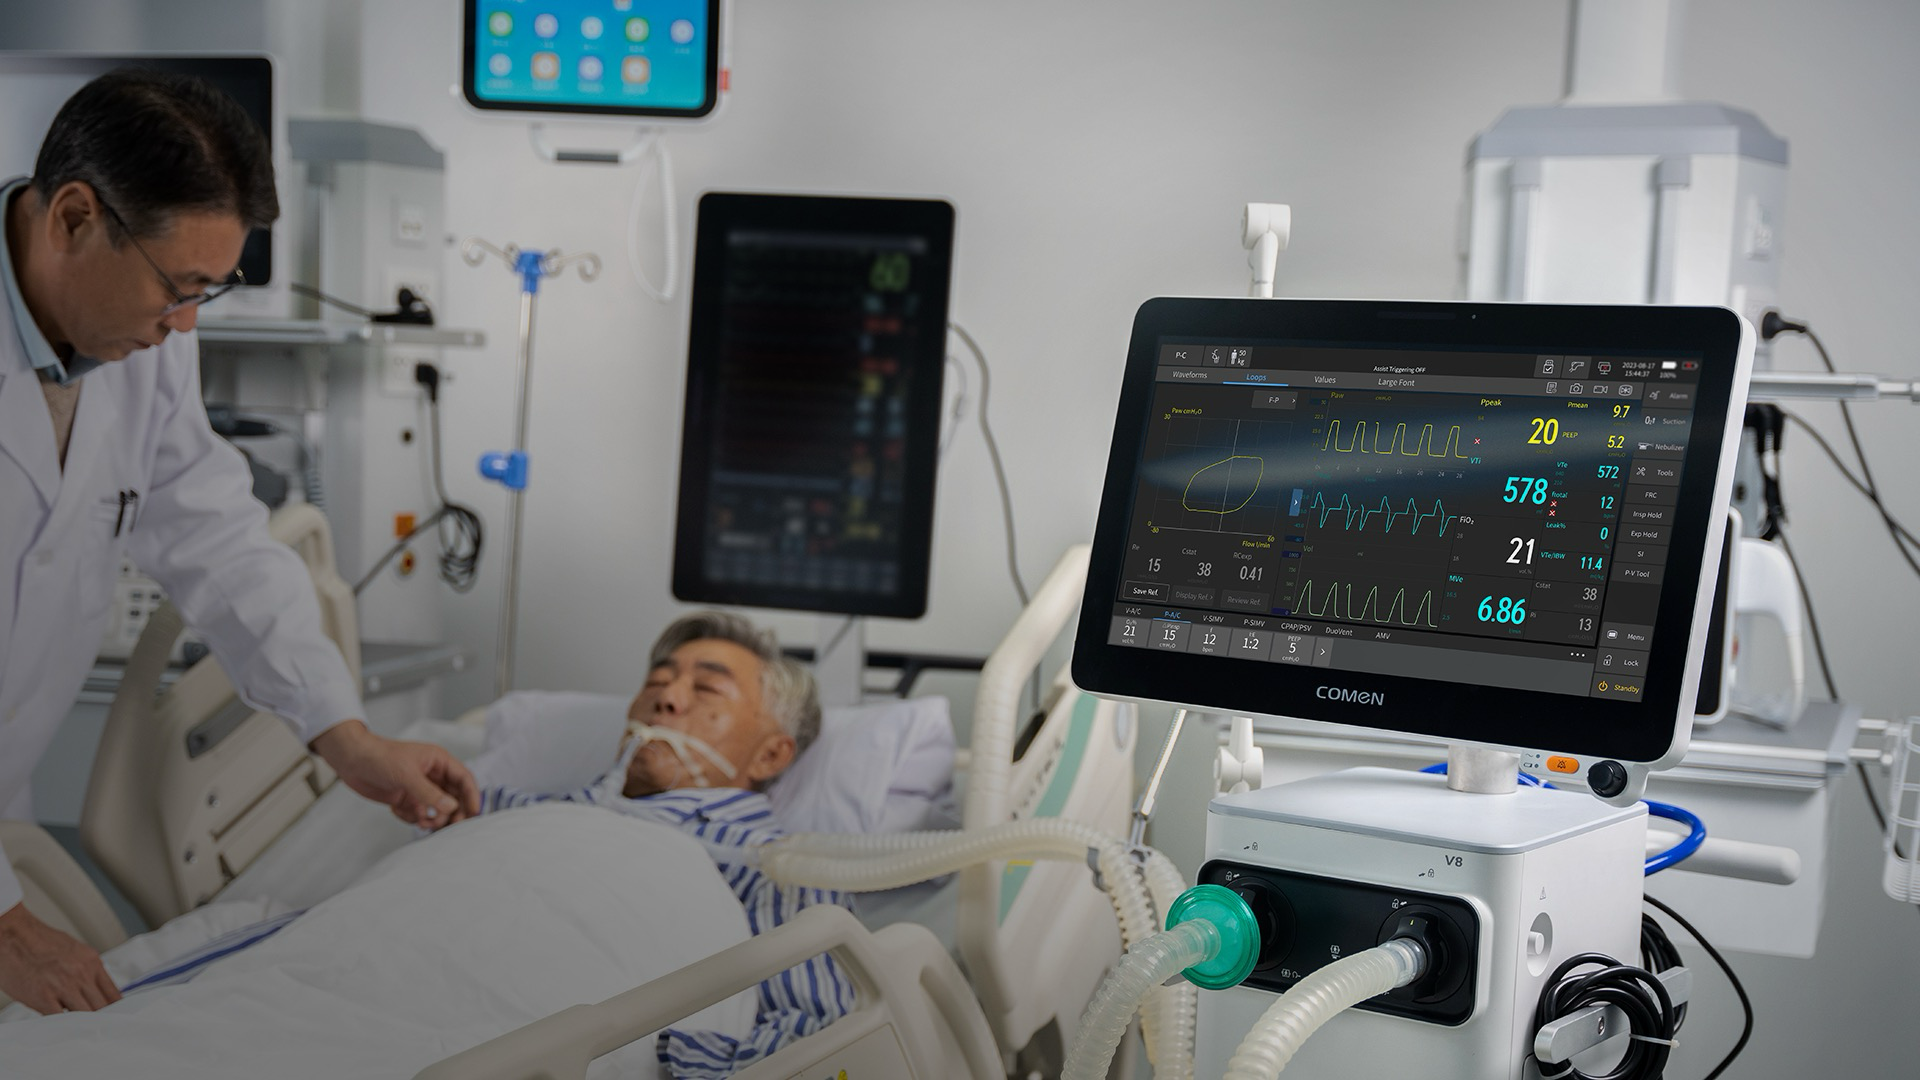
Okay—switching gears. Now I lay out what actually works, from the shop floor to hospital floor, with tech-first moves that don’t sound like boardroom fluff. I recommend three measurable pivots: tighten validation windows (shorter, more frequent sterilization validation cycles), institute inline CNC machining checks with automated torque sensors, and adopt a modular OEM strategy for PCB assembly so a single failure doesn’t take down a device family. I’ve implemented modular boards on a ventilator line in Manhattan in late 2021—downtime dropped 36% within six months. That’s not hypothetical; that’s real numbers. Also, re-engage with your suppliers on biocompatibility certificates and get ISO 13485 audits scheduled quarterly—not annually—so compliance is alive, not dormant. (Yes, it costs time. But the alternative is worse.)
What’s Next
We compare scenarios: keep patching, or redesign with resilience in mind. I favor redesign—component standardization reduces SKU complexity; predictive maintenance via simple telemetry cuts surprise failures; and a clear OEM playbook speeds recalls and repairs. When I led a supply-chain overhaul for a Bronx clinic contract in 2022, switching to fewer standardized pump modules shaved three days off repair cycles and lowered spare-part inventory by 28%. Those are the levers you pull. Now, to choose a partner, measure these three things: mean time between failures (MTBF) post-deployment, time-to-repair (TTR) under real-world stress, and percentage of components covered by a single-source replacement. Use those metrics, test them on one product line for 90 days, and iterate. I’m telling you from hands-on runs and late-night fixes—this is how you stop firefighting and start upgrading. Interrupt—fix—repeat. Then scale. medical equipment manufacturing companie knows this grind. In the end, be ruthless about data, not opinions. COMEN